
Every referral checked twice. Every decision human.
Alto manages the journey from incoming referral to completed care. Independently validated. CE-marked Class I medical device. In active pilot deployment.
FROM INCOMING REFERRAL TO COMPLETED CARE

THE PROBLEM
The gap between referral and procedure is where capacity is lost
The path from referral to care is not a workflow; it is a chain of manual handoffs, each a failure point. Incomplete inputs, fragmented handoffs, and readiness issues discovered too late to protect the slot.
20 - 40 mins
admin per referral
1 in 3
referrals incomplete
x in x
cancelled late
10 – 15%
of referrals lost
Alto is the missing operating layer: every referral visible, verified, clinically prioritised, booking-ready, procedure-ready.
HOW IT WORKS
Alto closes the gap between referral and procedure
Five stages, from the moment a referral arrives to a patient who turns up prepared.
Stage 1: Visible
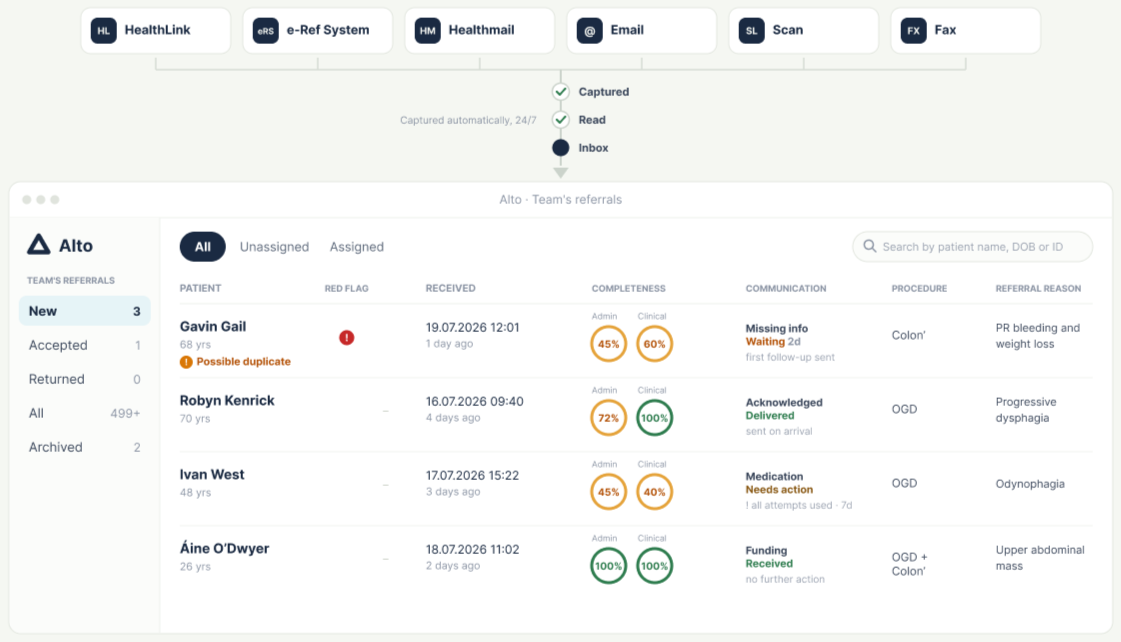
Every referral on the radar from the moment it arrives
Referrals land by HealthLink, email, post and fax, as forms, letters and scanned PDFs, and sit outside live reporting until someone opens them, whatever their urgency. Alto centralises every referral into one operational view on arrival, so demand and risk are visible.
Stage 2: Verified
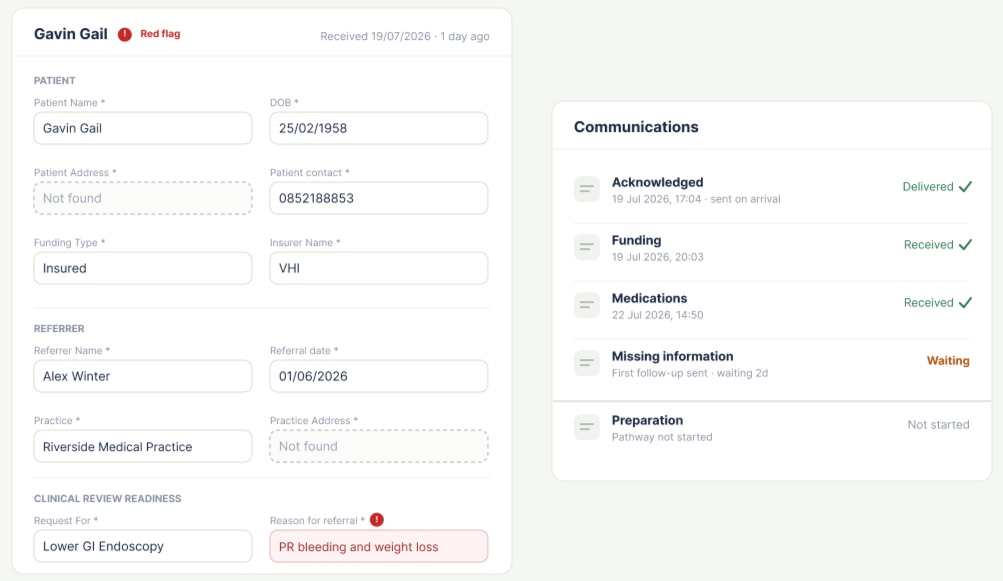
The administrative hour, done in minutes
Timestamping, patient matching, duplicate checks, acknowledgement, routing, completeness: this is where the administrative days go. Alto automates the stage. Missing information is flagged on arrival and chased automatically, duplicates resolved, routing handled. In minutes instead of most of an hour.
Stage 3: Prioritosed
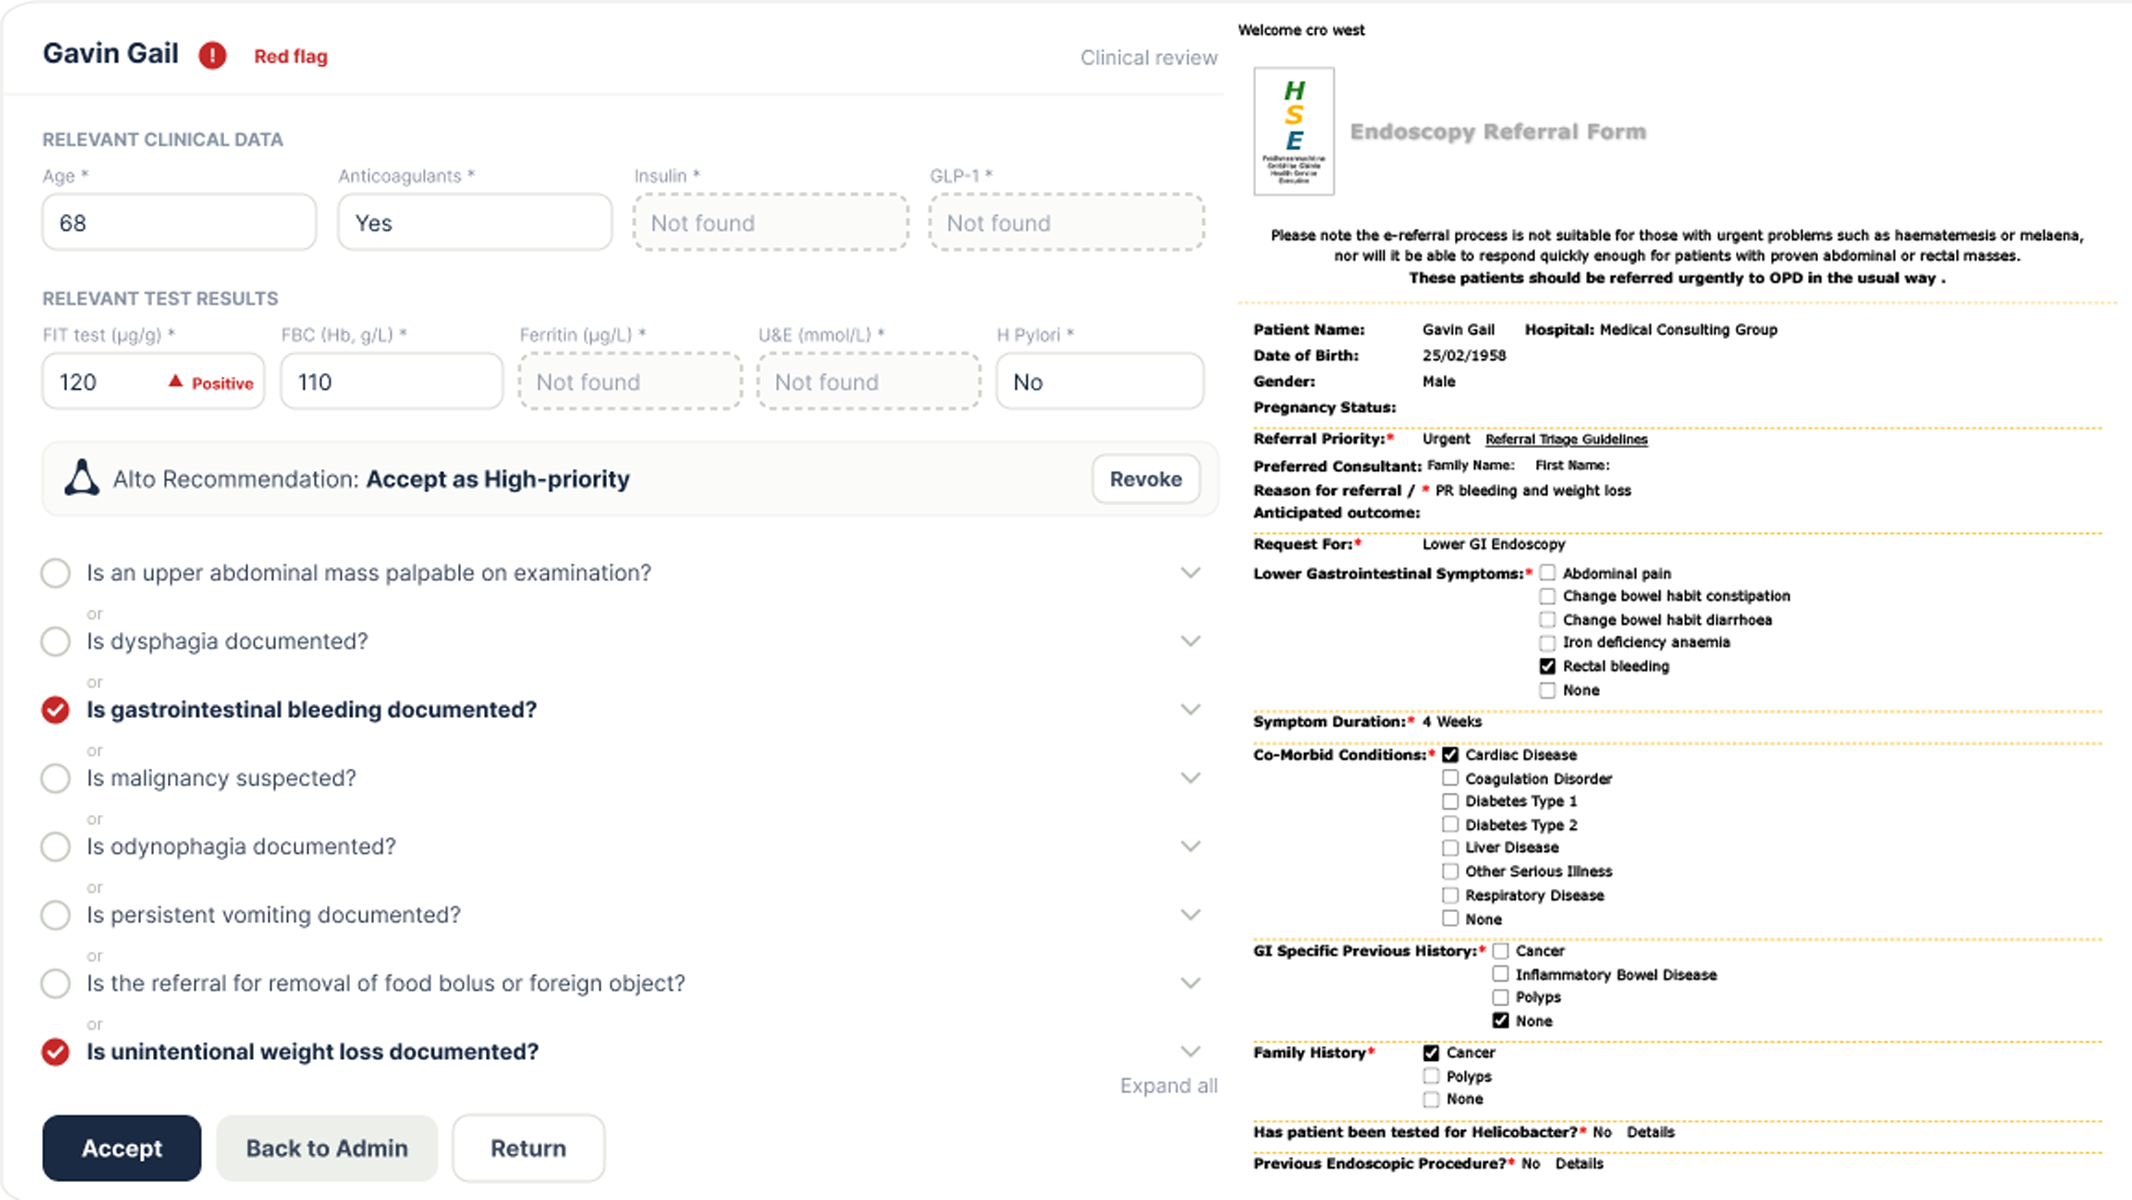
Urgent cases surface first, with the evidence shown
Clinical review often waits for batched, paper-based decisions, and delay turns booking into guesswork. Alto surfaces each referral with a decision-ready summary based on local protocols, in a prioritised queue, with transparent reasoning and evidence from the referral itself. No black box: the clinician acts or overrides.
Stage 4: Booking-Ready
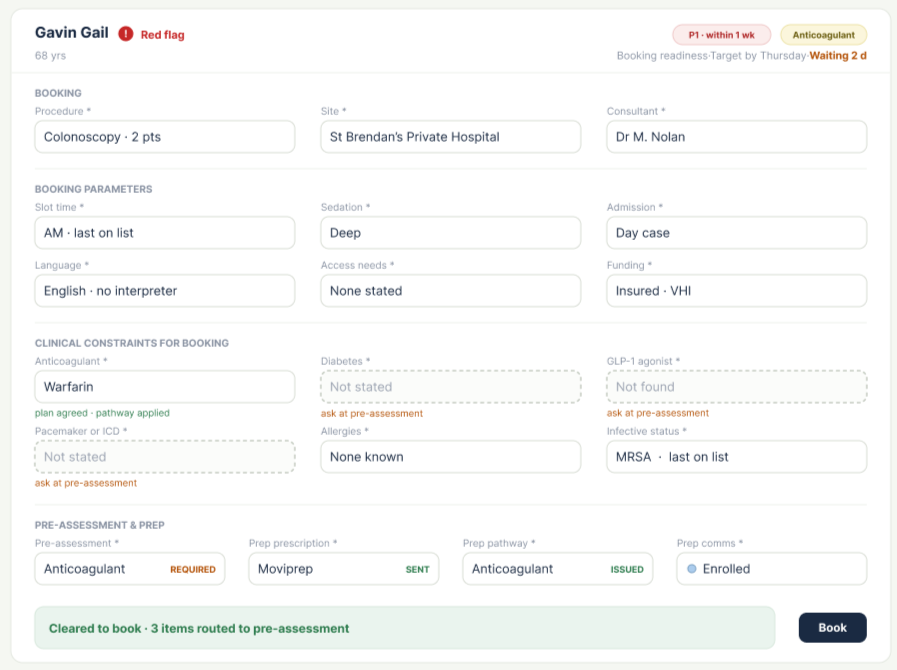
The right patient in the right slot, blockers cleared upstream
A slot needs the right type, clinician, site, equipment, sedation, preparation pathway, pre-assessment, insurance and lead time; unresolved, these surface too late to protect it. Alto clears the blockers upstream: the right patient in the right slot, preparation started.
Stage 5: Procedure-Ready
Patients arrive prepared, lists run full
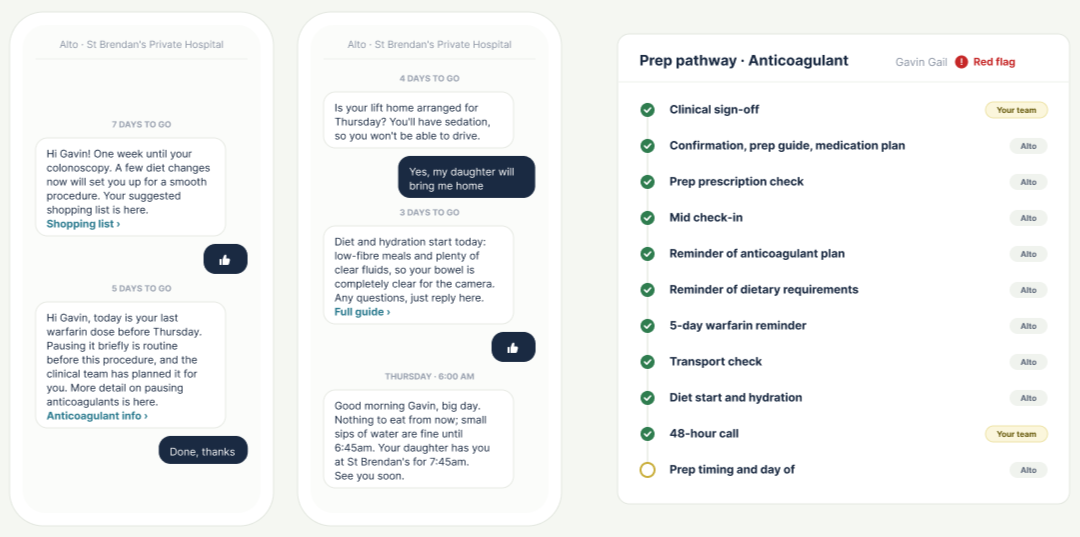
When preparation fails: late cancellations, non-attendance, repeat procedures, lost theatre time. In endoscopy alone, inadequate bowel preparation affects around one quarter of colonoscopies. Alto coordinates preparation proactively: chasing information, issuing instructions, updating referrers, supporting patients to arrive ready.
HOW IT'S SAFE
The Assistant & Judge Architecture

Your protocols. Alto arrives with a working protocol set: national guidelines, written up by our clinical team, reviewed by consultants. From there it becomes yours. Your criteria, your prioritisation standards, your preparation pathways. Every referral is then processed against your rules.
The Assistant reads every referral in any format, extracts the data, checks it against your administrative and clinical rules, and proposes the next action.
The Judge independently audits every output: catching errors, identifying low-confidence results, flagging ambiguous cases for human review. Faced with uncertainty it does not guess; it routes the file to a person, with a transparent evidence trail behind every decision, so the responsible clinician keeps full visibility and accountability.
Your team makes every decision. Final say stays with you.

EVIDENCE
Built on evidence, deployed with discipline
92.4%
accuracy across 6,084 data points
98.6%
under gold-standard clinician consensus
3
university
partnerships
2025/26
HIHI AI Innovation winner
A University of Galway study measured Alto against expert clinical judgement across 6,084 data points: 92.4% accuracy under the strictest single-reviewer standard, rising to 98.6% under gold-standard clinician consensus in follow-up analysis with Munster Technological University.
The cases expert reviewers saw differently, and the 1.4% we got wrong, are exactly what an independent second check layer is designed to catch. That finding shaped the Judge, strengthened further with Ulster University.
Nothing goes live unproven: synthetic data, then the hospital's own historic referrals, then shadow mode, then live. Alto is in clinical pilot with a private hospital partner and Health Innovation Hub Ireland at University College Cork.
FITS YOUR STACK
Nothing new for referrers.
Nothing ripped out for you.
In: your existing channels.
Referrals keep arriving exactly as they do today: HealthLink, Healthmail and email, fax, post and scans. Alto captures them from those channels on arrival; referrers change nothing and need nothing new.
Out: your existing systems.
Alto passes clean, structured data to your EHR or PMS in real time. Built on FHIR; integrates with Meditech, System C and Dedalus.
Full security and compliance detail on Safety and Governance →

MODULAR
Start where it hurts. Expand as it proves itself.
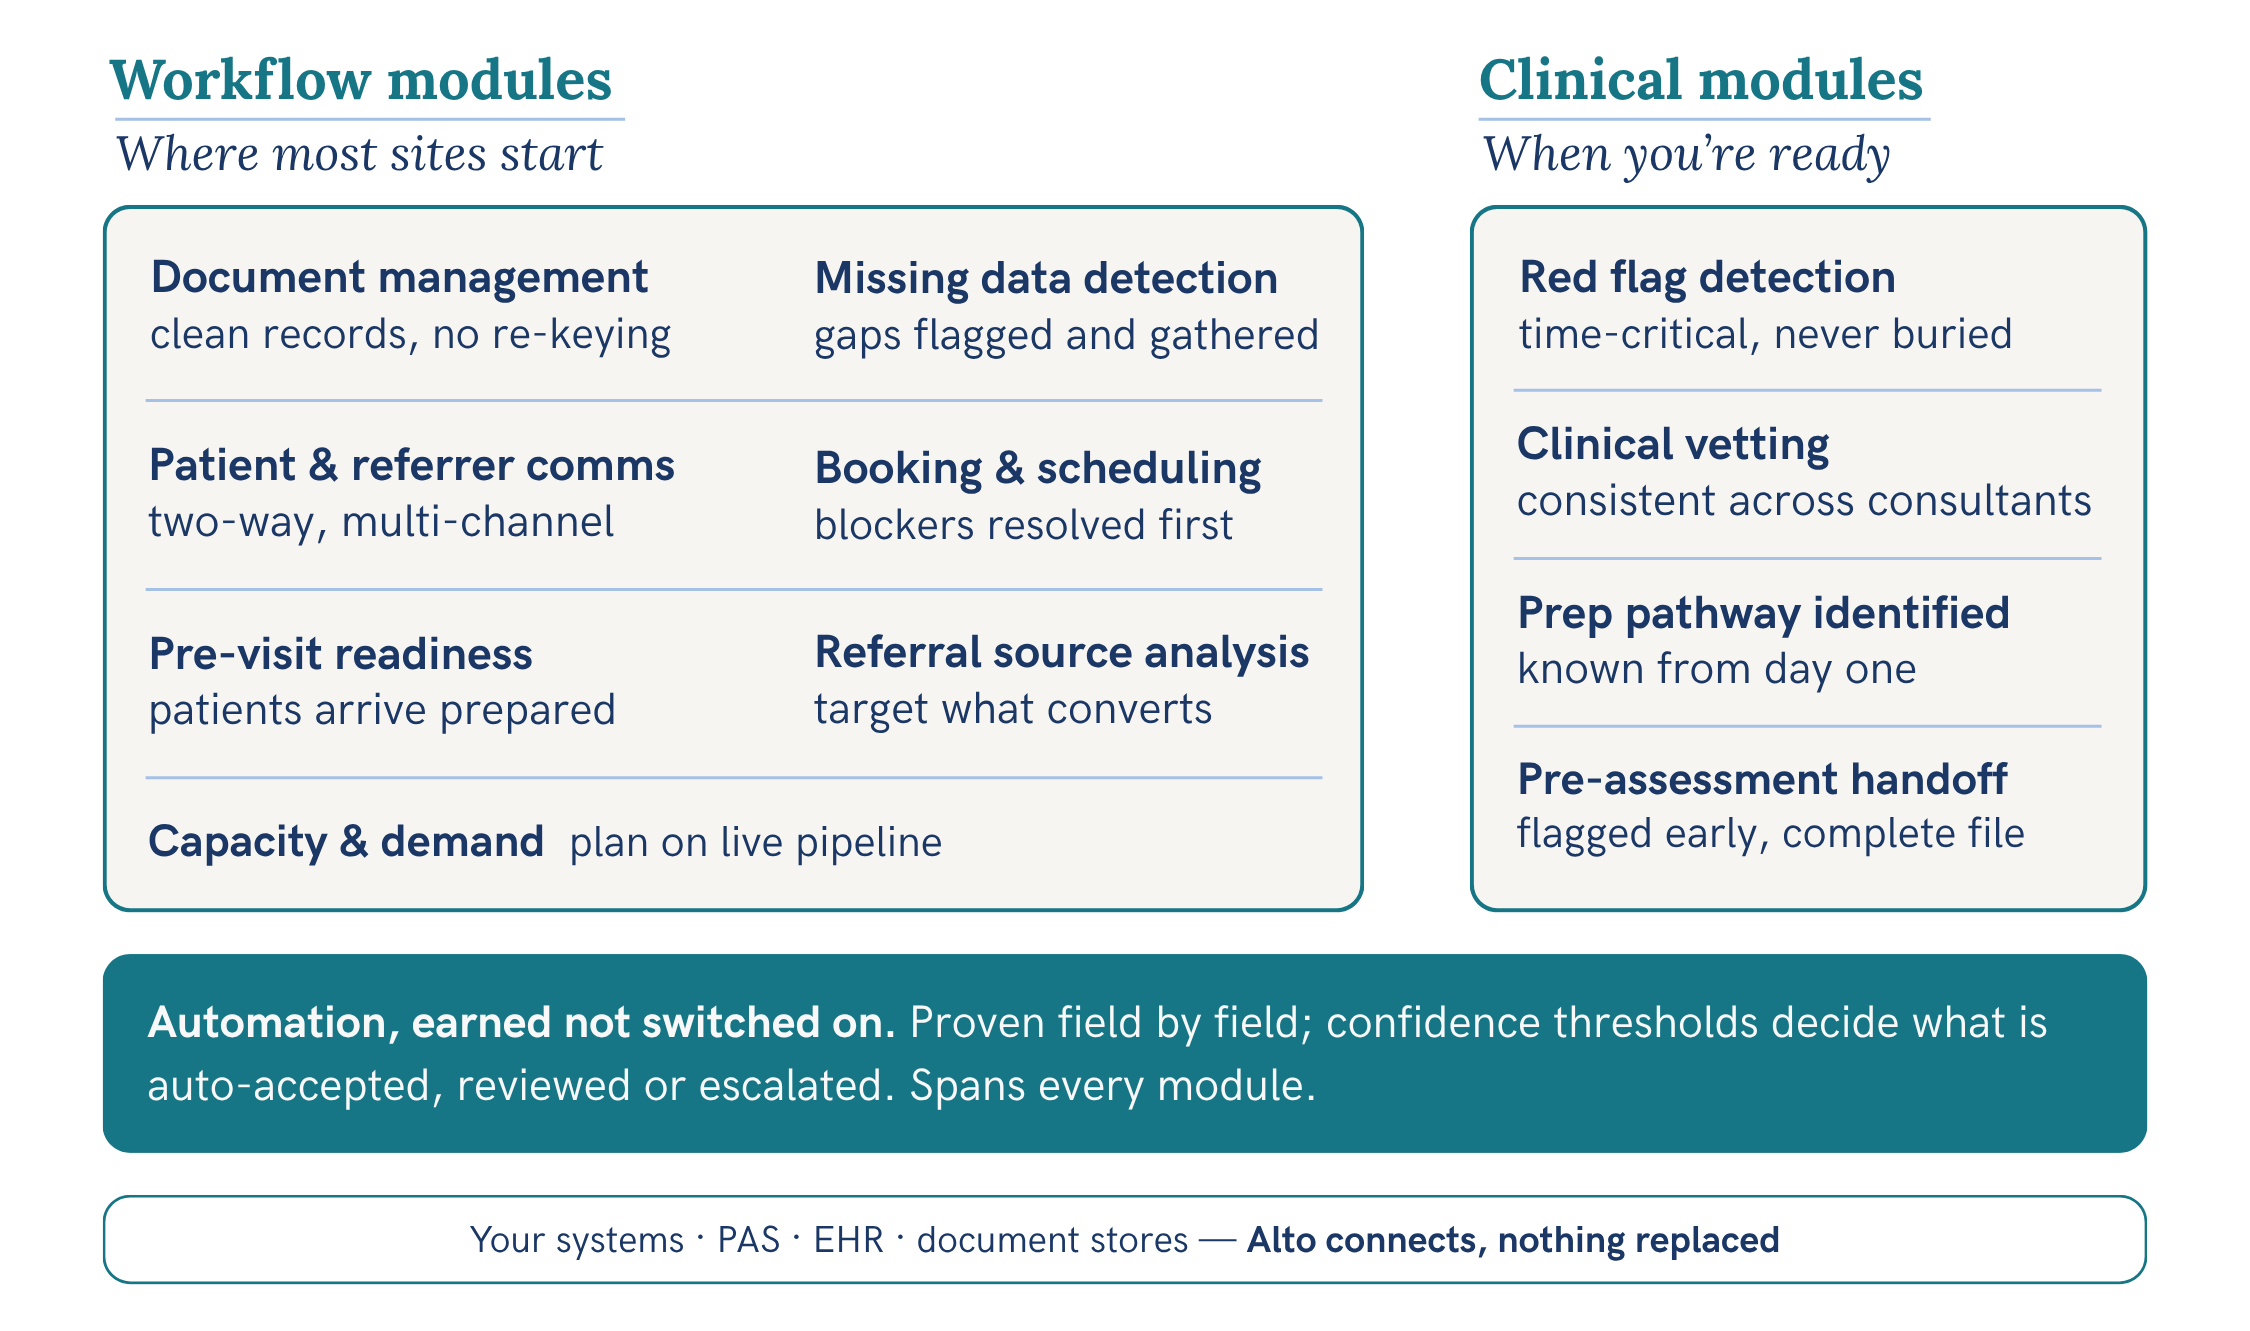
Alto is one platform sold in modules, so you enter at your most painful problem, at the risk level your governance is comfortable with, and add from there. No rip-and-replace, and every module clears the same staged validation before it goes live.
RAELA TO DRAFT
Workflow modules and Clinical modules intro paragraph


MODULAR
Start where it hurts. Expand as it proves itself.
Alto is one platform sold in modules, so you enter at your most painful problem, at the risk level your governance is comfortable with, and add from there. No rip-and-replace, and every module clears the same staged validation before it goes live.
Workflow modules, where most sites start:
Document management: referrals from any channel turned into clean records, no re-keying; one live surface for backlog, workload and audit trail.
Missing data detection: gaps flagged and gathered before they hold up a booking.
Patient and referrer communications: two-way, multi-channel confirmation, collection and updates.
Booking and scheduling: cleared referrals moved into the right slot, with the blockers resolved first.
Pre-visit readiness: patients guided through preparation, reducing cancellations and aborted procedures.
Referral source analysis: which channels and referrers perform, so outreach targets what converts.
Capacity and demand: live pipeline visibility, so staffing and list planning follow demand rather than guess it.
Clinical modules, added when you're ready:
Red flag detection and priority tracking, so time-critical cases are never buried.
Red flag detection and priority tracking, so time-critical cases are never buried.
Clinical vetting standardised across consultants: consistent, auditable decisions.
Prep pathway identified: the right preparation pathway assigned from the referral itself; sedation, medications and prep requirements known from day one, not discovered at booking.
Pre-assessment handoff: patients who need pre-assessment flagged early and handed over with a complete file, so the appointment confirms readiness rather than starting the search for it.
Automation is earned, not switched on.
As accuracy is proven field by field, Alto handles the highest-confidence, lowest-risk work automatically and routes everything else to a person. Explicit confidence thresholds decide what is auto-accepted, reviewed or escalated, so oversight relaxes only where the evidence earns it.
SEE IT RUN
You've seen how it works. Now see it on your referrals.
A live walkthrough of intake, prioritisation and handoff, tailored to your hospital or clinic. Or start with the audit: what your referral pathway is really costing you, from your own data.